
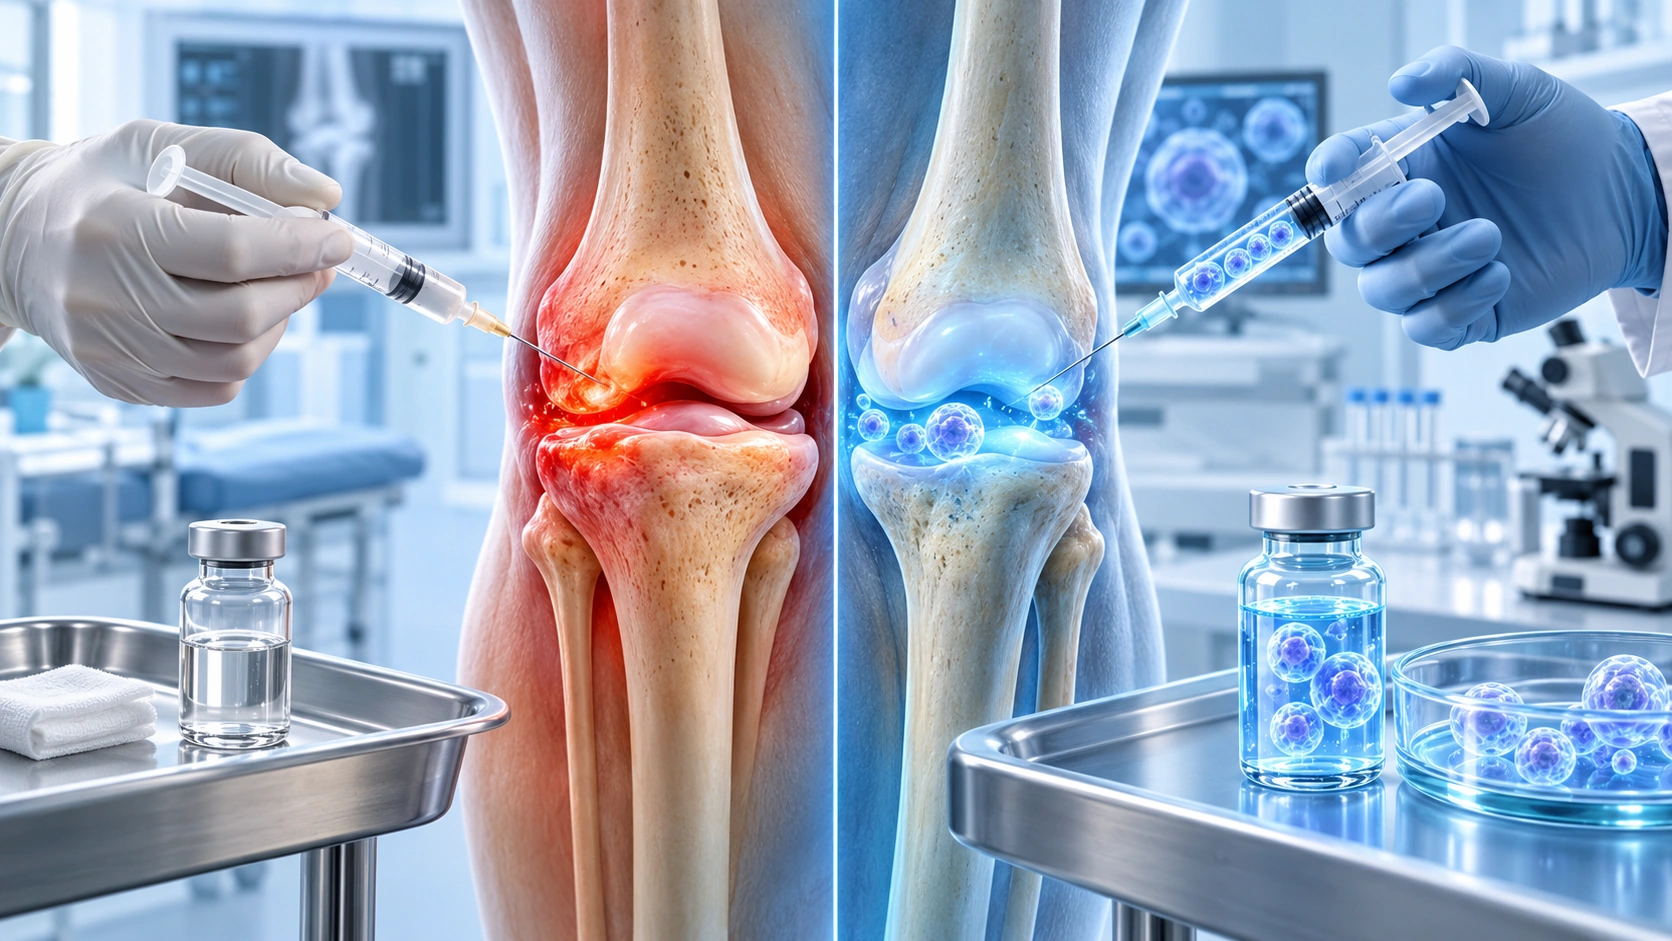
When joint pain begins interfering with walking, exercise, work, sleep, or everyday movement, injections may become part of the treatment conversation. Two options people often compare are stem cell therapy vs cortisone injection, but they are very different approaches.
Cortisone injections are established anti-inflammatory treatments used to reduce pain and inflammation for a limited period. Stem cell procedures fall within regenerative medicine and are being investigated for orthopedic problems, but the evidence, preparation methods, regulatory status, and expected outcomes are much less standardized.
That difference matters. Choosing between injections should start with the cause of the joint pain, the amount of structural damage, previous treatment, general health, and the patient’s goals rather than assuming one injection is automatically better.
Stem Cell Therapy vs Cortisone Injection: The Short Answer
Cortisone primarily aims to reduce inflammation and provide temporary symptom relief. Stem cell procedures are biologic treatments being studied for their potential effects on the joint environment and tissue repair processes, but they do not have the same level of established clinical guidance for osteoarthritis.
For symptomatic knee osteoarthritis, the American Academy of Orthopaedic Surgeons states that intra-articular corticosteroid injections can provide short-term relief. The American College of Rheumatology’s September 14, 2026 osteoarthritis guidance also includes consideration of intra-articular glucocorticoid injections among its major recommendations.
Stem cell therapy has a different evidence and regulatory position. The FDA states that regenerative medicine therapies, including stem cell products, have not been approved for orthopedic conditions such as osteoarthritis, knee pain, hip pain, shoulder pain, back pain, or tendon problems.
| Comparison | Cortisone Injection | Stem Cell Therapy |
|---|---|---|
| Main purpose | Reduce inflammation and pain | Investigational biologic approach intended to influence regenerative or healing processes |
| Evidence for osteoarthritis | Established evidence for short-term symptom relief | Evidence remains inconsistent and protocols are not standardized |
| Regulatory position | Commonly used medical treatment, depending on the drug and clinical indication | No FDA-approved stem cell products for orthopedic conditions |
| Expected timing | Relief may begin within days after the injection | No single predictable response timeline |
| Duration | Usually temporary and varies by patient | Duration and degree of benefit are not reliably established |
| Main limitation | Does not repair the underlying structural damage | Uncertain effectiveness, variable products, protocols, and regulatory considerations |
The comparison becomes more useful once the actual source of the joint pain is understood.
Why the Diagnosis Matters More Than the Injection Name
“Joint pain” describes a symptom, not a diagnosis. Arthritis, cartilage degeneration, bursitis, tendon problems, ligament injuries, meniscus damage, inflammatory disease, and other conditions can all cause pain around a joint.
Someone with an inflamed arthritic knee may need a very different treatment plan from someone with a meniscus tear or unstable ligament. Even among people with joint arthritis, the severity and location of the disease can change which options make sense.
Osteoarthritis is especially relevant to this comparison. It involves progressive changes within the joint, including cartilage deterioration and changes to other joint structures. An injection may reduce symptoms, but symptom relief does not necessarily mean the underlying structural problem has been reversed.
That is why an orthopedic evaluation may include symptom history, physical examination, previous treatment response, imaging, activity limitations, and medical conditions before an injection is discussed. Cendant’s broader orthopedic treatment information explains the types of musculoskeletal conditions that may be evaluated when patients are considering nonsurgical options.
How Cortisone Injections Reduce Joint Pain
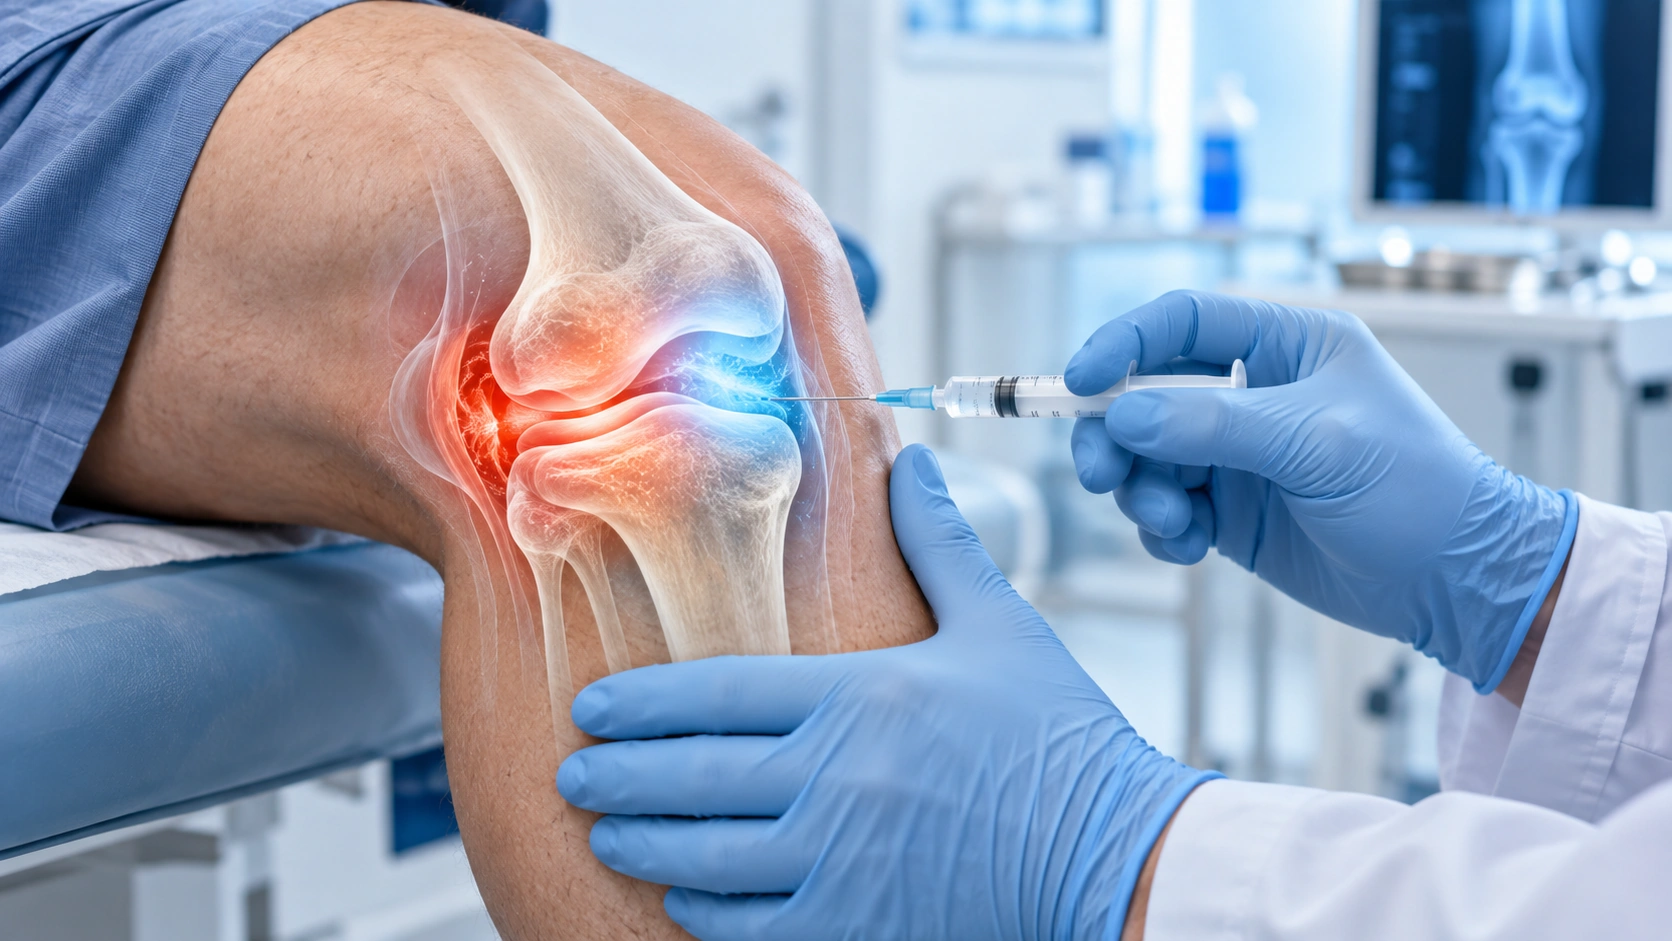
Cortisone injections contain a corticosteroid medication delivered into or around an affected joint. Corticosteroids suppress inflammatory activity, which can reduce swelling, irritation, and pain.
Why relief can happen relatively quickly
Inflammation contributes to pain in many joint conditions. When a corticosteroid reduces that inflammatory response, symptoms can become easier to manage even though the underlying arthritis or structural damage is still present.
Mayo Clinic notes that cortisone injections are used for conditions including osteoarthritis, rheumatoid arthritis, bursitis, gout, and tendinitis. Relief varies according to the condition being treated.
For knee osteoarthritis specifically, AAOS describes intra-articular corticosteroids as an option for short-term relief. Its evidence review found improvement in pain and function, with effects lasting up to about three months in the studies it evaluated.
What cortisone does not do
A reduction in pain is not evidence that cartilage has regrown or that arthritis has been eliminated.
Imagine a person with knee arthritis who has significant inflammation after walking or standing. A cortisone injection might decrease that inflammatory pain enough to improve daily function for a period. The degenerative changes visible in the knee, however, may still remain.
This distinction between symptom control and structural disease becomes important when comparing cortisone with regenerative procedures.
What Stem Cell Therapy Is Trying to Address
Stem cells are discussed in regenerative medicine because certain cell populations can participate in biological signaling, tissue maintenance, and repair processes. That scientific interest has led researchers and clinicians to study cell-based approaches for orthopedic conditions.
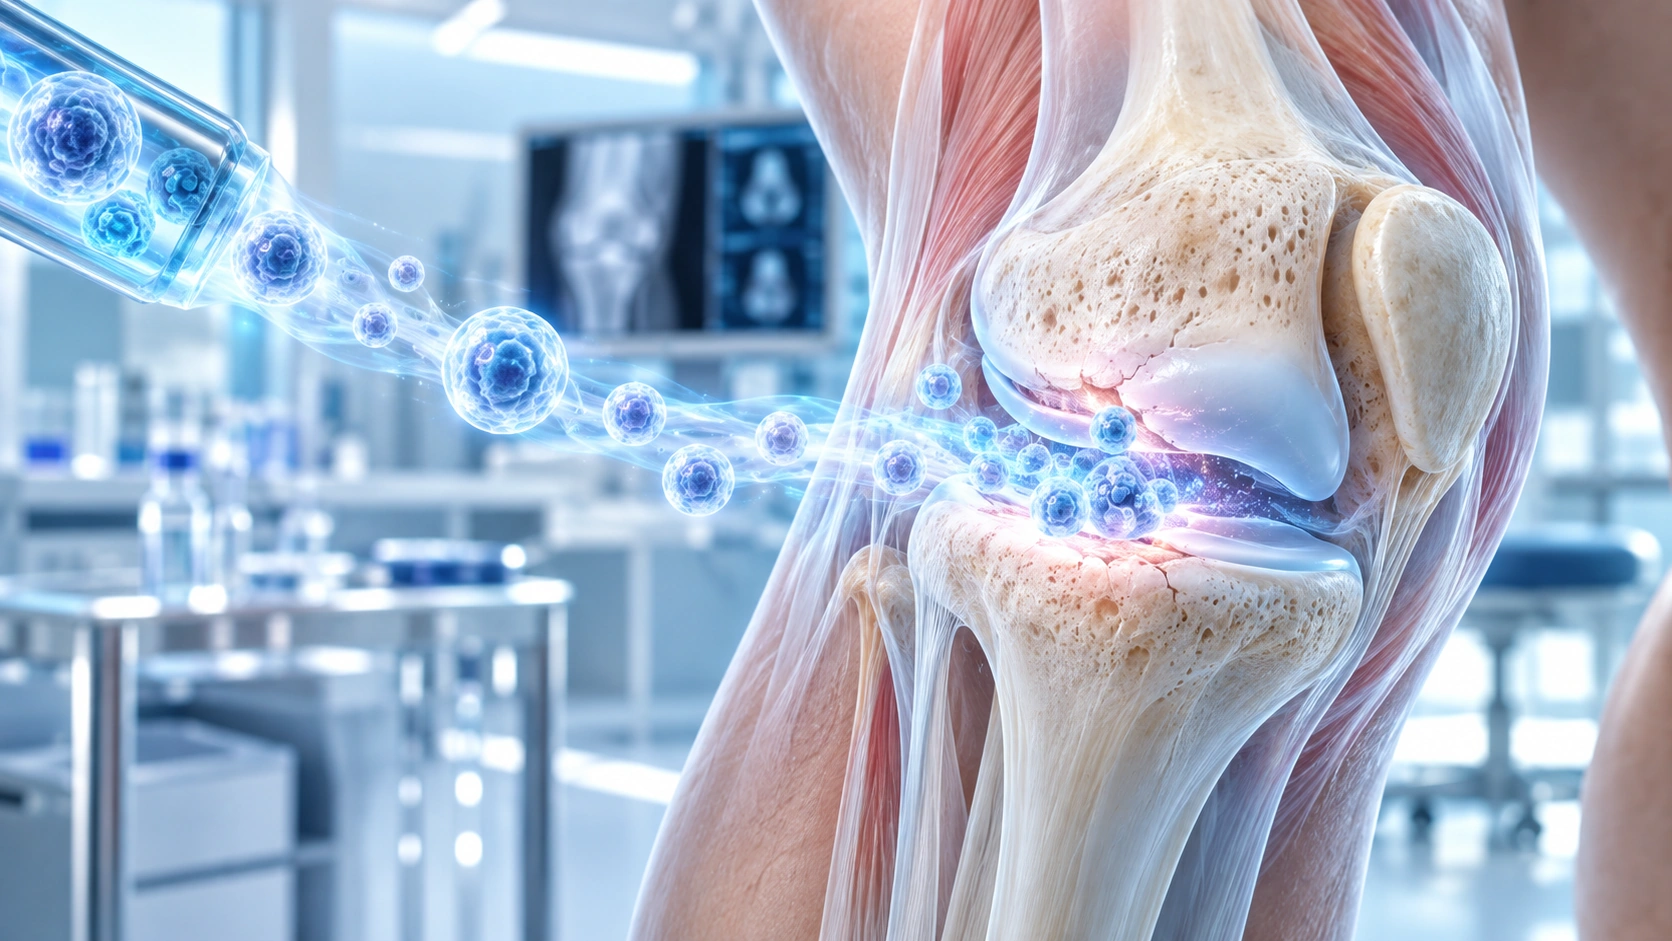
Anyone new to the subject can review Cendant’s regenerative medicine and stem cell therapy guide for broader background on regenerative treatment concepts.
The important point is that “stem cell therapy” does not describe one standardized injection. Cell source, preparation, processing, concentration, accompanying substances, injection technique, patient selection, and the condition being treated can vary.
Those differences make comparisons between studies difficult.
Regenerative intent is not the same as proven regeneration
Stem cell treatments are sometimes described as treatments that rebuild cartilage or restore damaged joints. That conclusion should not be assumed.
Research is examining whether certain cell-based treatments can influence pain, inflammation, joint biology, and tissue responses. Clinical improvement in pain or function does not automatically prove that new cartilage has formed or that osteoarthritis has been reversed.
The FDA specifically states that regenerative medicine therapies have not been approved for orthopedic conditions including osteoarthritis and common forms of joint pain.
Patients considering stem cell therapy for joint pain should therefore ask exactly what product or procedure is being proposed and what evidence applies to their diagnosis.
Cortisone vs Stem Cells: What the Evidence Currently Shows
The evidence supporting cortisone and stem cell injections is not at the same stage.
For symptomatic knee osteoarthritis, corticosteroid injections have enough clinical evidence to appear in established treatment guidelines. AAOS characterizes their benefit as short term, while the latest ACR osteoarthritis update continues to include intra-articular glucocorticoid injections among treatments clinicians may consider as part of individualized care.
Stem cell injections remain more uncertain.
The 2019 ACR and Arthritis Foundation osteoarthritis guideline strongly recommended against stem cell injections for knee and hip osteoarthritis, citing substantial variation in available preparations and techniques.
That recommendation reflects an evidence problem that still matters when evaluating regenerative procedures: two treatments both called “stem cell therapy” may not actually be equivalent.
Regulatory status must also be separated from research interest. The FDA states that no regenerative medicine therapies have been approved for orthopedic conditions such as osteoarthritis, knee pain, hip pain, or shoulder pain.
This does not mean that research into cell-based orthopedic treatments has stopped. It means patients should distinguish promising biological research from a treatment whose safety and effectiveness have been established for a specific orthopedic indication.
How Pain Relief and Recovery Expectations Differ
Patients often ask which injection lasts longer. There is no dependable universal answer because the treatments work differently and individual responses vary.
Cortisone focuses on symptom control
Cortisone can reduce inflammatory pain without correcting the mechanical or degenerative cause of the problem.
For some people, temporary symptom reduction can still be useful. It may make daily activity easier or allow greater participation in rehabilitation. For others, relief may be limited or short lived.
Repeated injections also require caution. Mayo Clinic notes that healthcare professionals commonly limit cortisone injections because larger doses and repeated use can increase the likelihood of adverse effects.
Stem cell outcomes are less predictable
There is no standardized timeline for when an orthopedic stem cell procedure should begin working or how long an effect should last.
Differences in the injected material, diagnosis, disease severity, treatment technique, rehabilitation, and individual biology make precise promises inappropriate.
Someone researching stem cell therapy for knee osteoarthritis should therefore be cautious about guarantees involving cartilage regrowth, permanent pain relief, or a specific recovery schedule.
Realistic expectations should be based on the exact treatment being offered and the evidence supporting it.
Risks and Limitations Deserve as Much Attention as Potential Benefits
Any injection into a joint involves potential risks.
Cortisone has decades of clinical use, so its potential adverse effects are relatively well characterized. Possible problems include temporary pain after injection, infection, temporary increases in blood sugar, skin or soft-tissue changes, tendon weakening, and concerns about cartilage damage with repeated injections.
The risk profile of stem cell therapy is harder to describe with one list because products and processing methods vary considerably.
The FDA has warned that unapproved regenerative medicine products have been associated with serious safety problems, including bacterial infections and other significant adverse events.
That makes several practical questions important before treatment:
- What exactly is being injected?
- Where does the material come from?
- How is it collected and processed?
- What evidence supports its use for this specific diagnosis?
- What is its FDA regulatory status?
- What complications have been reported?
- What established alternatives should also be considered?
Patients should also discuss medications, diabetes, infection risk, bleeding risk, previous injections, and other medical conditions with the clinician performing the procedure. Prescribed treatment should not be stopped or changed without guidance from the appropriate healthcare professional.
The Joint Being Treated Can Change the Decision
Research and clinical recommendations cannot automatically be transferred from one joint to another.
The knee has received considerable research attention, but joint structure, disease progression, injection technique, and available evidence differ across the body.
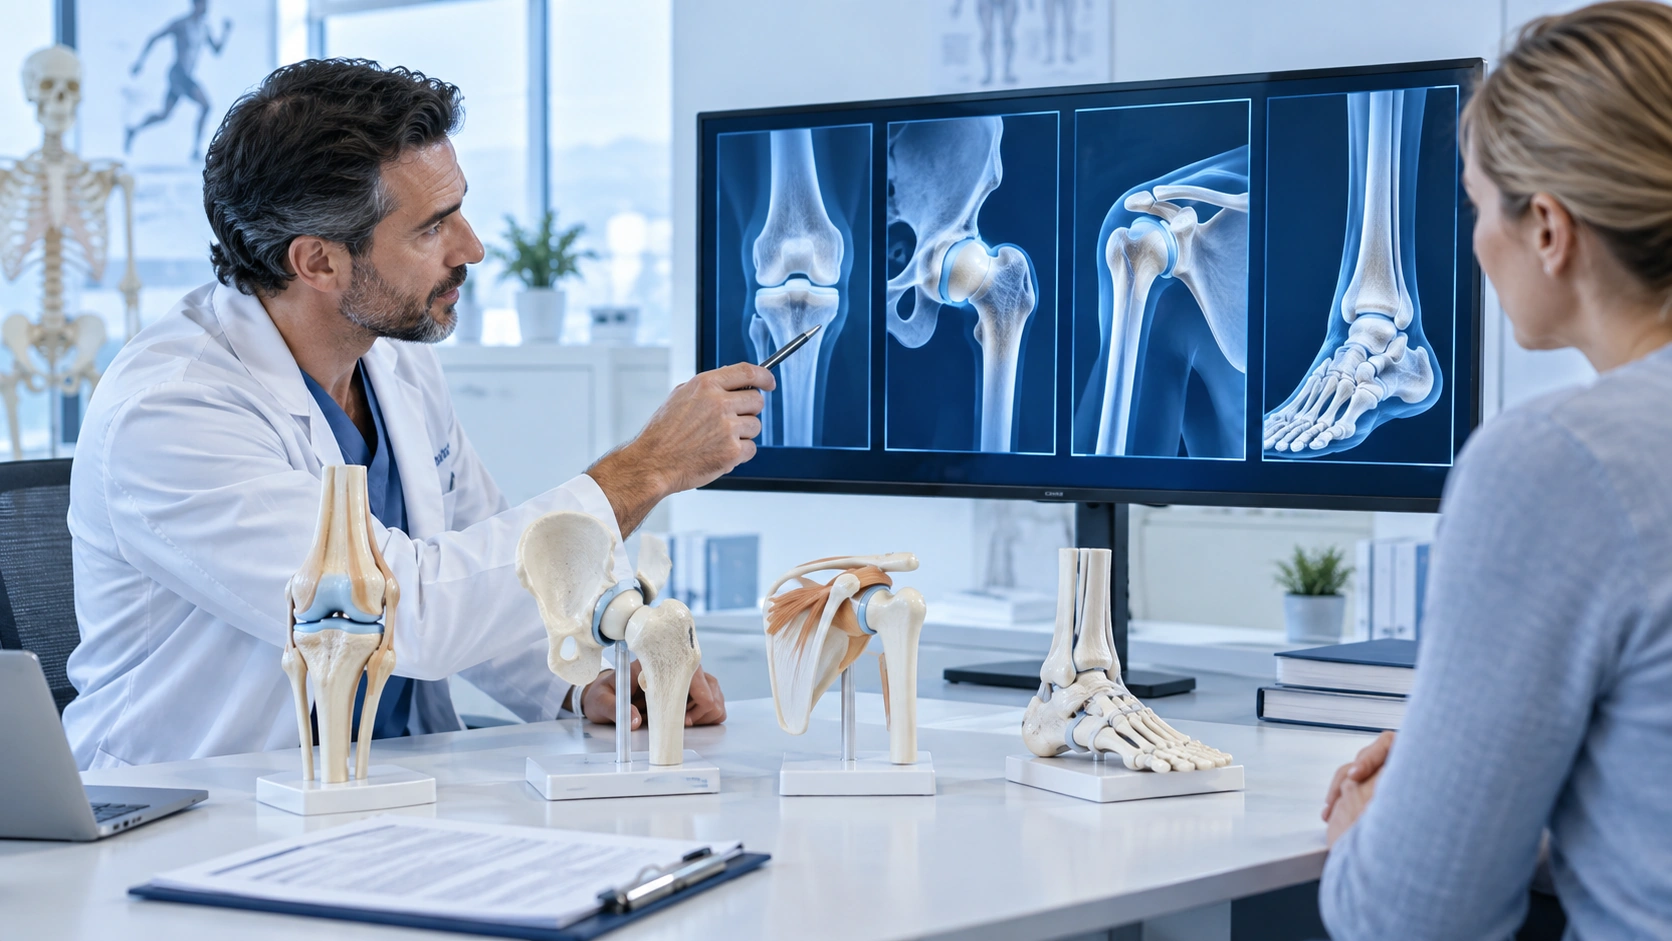
For example, someone with hip arthritis may face different treatment considerations from someone with knee osteoarthritis. Hip injections also commonly require image guidance because of the depth and anatomy of the joint.
A person with shoulder arthritis may have pain from the joint itself, the rotator cuff, bursae, tendons, or a combination of structures. Treating the wrong pain generator can make any injection appear unsuccessful.
This is another reason a diagnosis should come before choosing between cortisone, regenerative medicine, rehabilitation, medication, or other treatment.
Where PRP Fits Into the Cortisone and Stem Cell Conversation
People researching regenerative treatments frequently encounter another comparison: PRP vs cortisone.
Platelet-rich plasma, or PRP, is not stem cell therapy. PRP is prepared from a patient’s blood and contains a concentrated portion of platelets along with associated signaling proteins and growth factors.
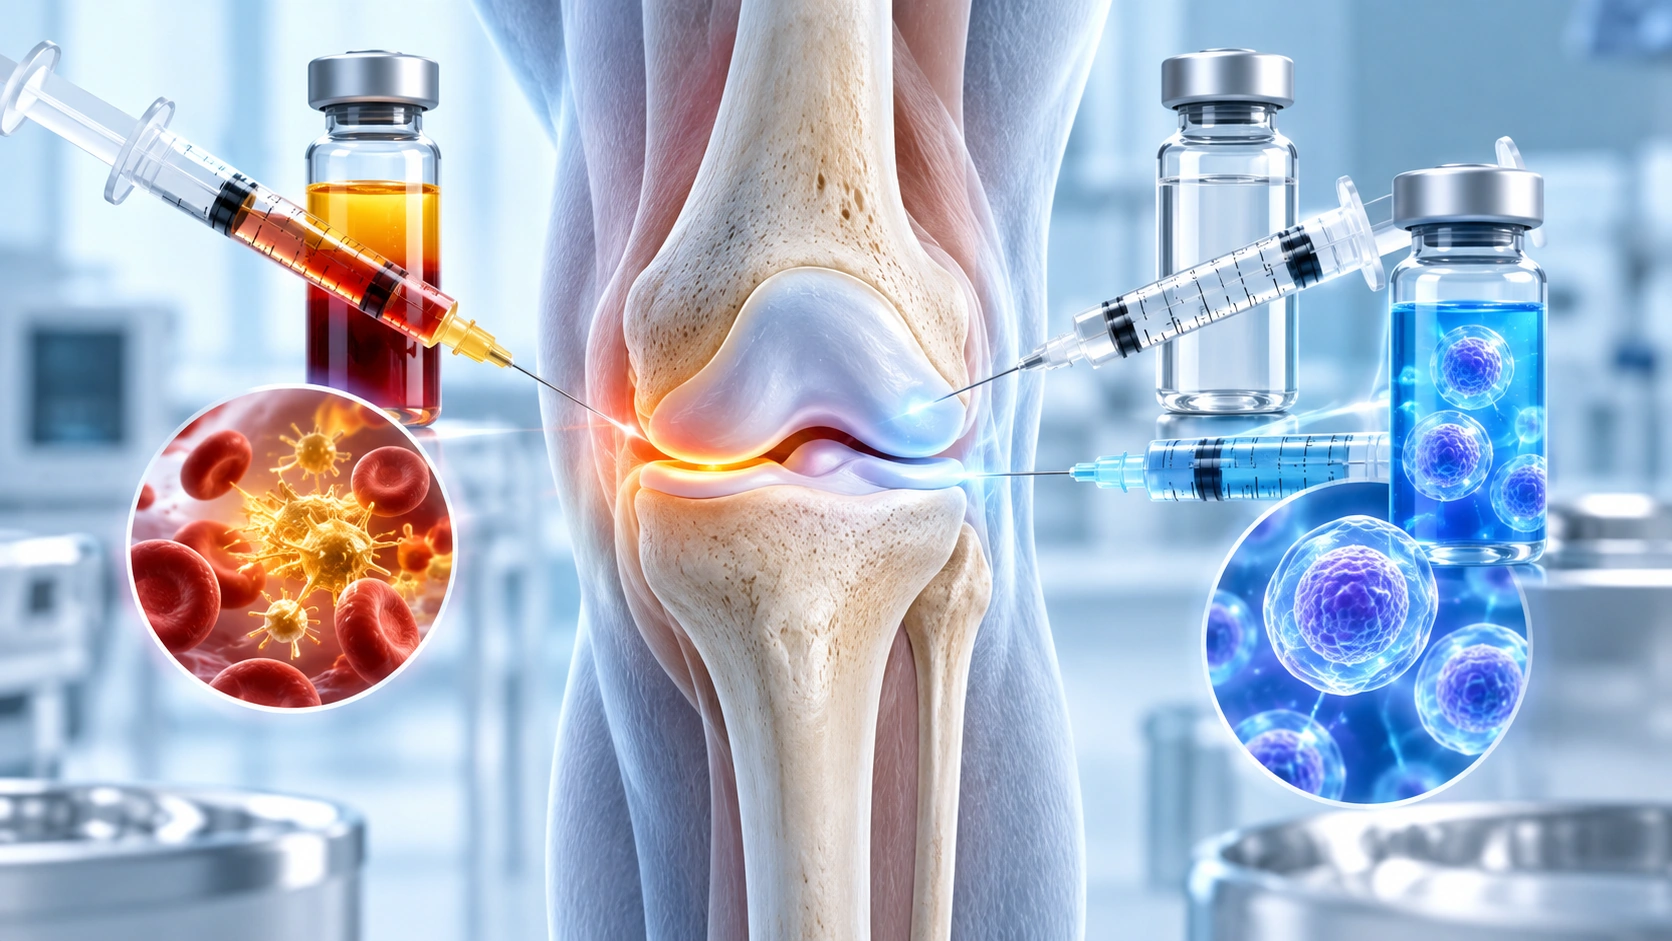
Stem cell procedures involve cell-based products or preparations with different biological characteristics.
These approaches should not be grouped together simply because both are commonly discussed under regenerative medicine. Evidence can differ according to the therapy, joint, diagnosis, and preparation technique.
Someone comparing cortisone, PRP, and stem cell procedures may find it useful to first understand how regenerative medicine works before evaluating the claims attached to a particular injection.
The practical question is not simply, “Which injection is regenerative?” It is, “What evidence supports this exact treatment for my exact condition?”
When Cortisone May Enter the Treatment Plan
Cortisone may be discussed when inflammation is contributing significantly to pain and short-term symptom reduction could improve function or make rehabilitation more manageable.
Current osteoarthritis guidance does not treat injections as the entire treatment plan. The ACR’s September 2026 guidance emphasizes exercise, self-management, weight management when appropriate, medications when clinically suitable, and shared decision-making alongside injectable treatments.
That broader approach matters because osteoarthritis often requires ongoing management rather than one isolated procedure.
A person whose knee feels considerably better after cortisone, for example, may still need strengthening, activity modification, weight management when relevant, treatment of biomechanical problems, or other strategies intended to protect function.
Cortisone can therefore be useful without being curative.
When Someone Is Considering Stem Cell Therapy
Interest in stem cell therapy often increases when joint pain persists despite conservative treatment or when someone wants to investigate nonsurgical options before considering an operation.
That interest is understandable, but the decision requires a different type of discussion from choosing an established anti-inflammatory injection.
Disease severity matters. So do age, general health, the amount of structural damage, previous surgery, the exact source of pain, activity goals, and what other treatments have already been attempted.
Most importantly, patients should understand the investigational and regulatory context. The FDA advises consumers to ask whether a regenerative medicine product has been reviewed or approved for the proposed use and to be cautious of claims that an unapproved product can safely and effectively treat orthopedic disease.
A responsible consultation should therefore explain uncertainties as clearly as potential benefits.
Discussing Nonsurgical Options for Joint Pain
The choice between stem cell therapy and cortisone injections is rarely a simple contest between two needles.
Cortisone has established clinical use for reducing inflammation and can provide short-term relief for certain joint conditions, including symptomatic osteoarthritis. Its effects are usually temporary, and repeated treatment carries limitations.
Stem cell therapy approaches joint problems from a different biological direction, but orthopedic applications remain investigational, treatment methods vary, and the FDA has not approved stem cell products for orthopedic conditions. Current evidence does not support promises of predictable cartilage restoration or permanent relief.
For someone living with ongoing joint pain, the most useful next question is not necessarily, “Which injection should I get?” It is, “What is causing my pain, how advanced is the problem, and which nonsurgical options fit my diagnosis and goals?”
Cendant Stem Cell Center evaluates patients exploring regenerative and other nonsurgical approaches to orthopedic problems. If joint pain is limiting movement or activity, you can discuss nonsurgical treatment options with Cendant Stem Cell Center and review the potential benefits, limitations, alternatives, and regulatory considerations that apply to your situation.